Congo’s Deadliest Ebola Outbreak Passes 8,000 Cases as Missed Contacts, Unpaid Responders and Attacks on Burial Teams Keep Bundibugyo Moving

Die Demokratische Republik Kongo hat mehr Ebola-Infektionen in einem Bundibugyo-Ausbruch bestätigt, als das Land jemals von irgendeiner Art des Virus registriert hat. Die von der European Centre for Disease Prevention and Control Die Maut wurde bis zum 26. September auf 8.067 bestätigte Fälle und 3.901 Todesfälle festgesetzt, eine grobe Todesrate von 48,4 Prozent. Weitere 773 Patienten waren isoliert, und 2.070 Personen, die positiv getestet wurden, hatten sich erholt. Das Bulletin fügte 78 Fälle und 49 Todesfälle an einem einzigen Tag hinzu: 57 der Neuinfektionen waren in Ituri, 17 in Nord-Kivu, drei in Haut-Uélé und eine in Bas-Uélé.
Die nationale Total verbirgt einen bewegenden Ausbruch. Ituri trägt immer noch das meiste davon, mit 6.155 bestätigten Fällen und 2.834 Todesfällen in 28 von 36 Gesundheitszonen. Nord-Kivu hat 1.523 Fälle und 906 Todesfälle in 16 von 34 Zonen, eine Todesrate von fast 60 Prozent. Haut-Uélé hat 331 Fälle und 139 Todesfälle. Kleinere Grafen sitzen in Tshopo, Bas-Uélé, Süd-Kivu und Sud-Ubangi. Dreiundsechzig von 167 Gesundheitszonen in diesen sieben Provinzen haben mindestens eine bestätigte Infektion gemeldet. Süd-Kivu hat seit dem 29. Mai keinen neuen Fall gemeldet.

Congo’s Ministry of Public Health, Hygiene and Social Welfare declared the outbreak on May 15 in Ituri, after deaths among health workers around Mongbwalu and Bunia. The Weltgesundheitsorganisation wurde am 5. Mai auf eine Krankheit mit hoher Sterblichkeit unbekannter Ursache aufmerksam gemacht. Das National Institute for Biomedical Research identifizierte das Bundibugyo-Virus. Am 17. Mai, der Generaldirektor Tedros Adhanom Ghebreyesus eine öffentliche Gesundheit Notstand von internationaler Bedeutung erklärt, und die afrikanischen Zentren für Krankheitskontrolle und Prävention Es wurde als kontinentaler Sicherheitsnotstand behandelt. Es ist der 17. Ebola-Ausbruch im Kongo seit 1976 und hat bereits die Epidemie 2018-2020 im Osten bestanden.
Bundibugyo ist nicht die Zaire-Art, die Ervebo und die lizenzierten Antikörper-Medikamente gebaut wurden, um zu stoppen. Es wurde zuerst in Ugandas Bundibugyo Bezirk in 2007-2008 anerkannt. Es gibt immer noch keinen lizenzierten Impfstoff und keine zugelassene spezifische Behandlung. Unterstützende Pflege rettet einige Patienten, die früh ankommen. Die WHO hat gewarnt, dass die Todesrate und insbesondere Todesfälle außerhalb von Behandlungszentren zeigen, wie viele Menschen immer noch zu spät gefunden werden.
That warning is now a surveillance failure. Africa CDC Director-General Jean Kaseya said contact lists were no longer a useful picture of the epidemic. With more than 7,000 confirmed cases by mid-September, about 32,000 people were being followed, only about 27 percent of the contacts that caseload should have produced. „It means 63 percent of those who must be in a contact list, we don’t know where they are,“ he said. Only about 19 percent of recent confirmed cases were people already known to tracers. From August 24 to September 13, community deaths were 69.2 percent of recorded deaths. „When you have cases coming from community, you cannot say that the outbreak is under control,“ Kaseya said. By September 26, ECDC reported that 74.7 percent of contacts already identified were under follow-up. That is a different problem from the people who never made a list.
On September 25, Tedros said the virus had a head start and that responders were still playing catch-up. There were encouraging signs, he said, and the epidemic was still far from over. A day earlier, WHO said transmission had reached Bulu in Sud-Ubangi and Dungu in Haut-Uélé, on the South Sudan border. As of September 23 the agency was working from 7,890 confirmed cases and 3,799 deaths. „It’s very difficult to see Ebola in isolation because even our response in Ebola is affected by the conflict because there is displacement and there is access problem to some areas,“ Tedros said.
North Kivu is where the shift shows up in the wards. Reporting from the province describes centers filling even as some Ituri zones reported fewer new infections. Africa CDC put North Kivu’s Ebola bed occupancy at 143.6 percent in mid-September, 316 patients against 220 beds. All 29 beds at Butembo’s Kitatumba center were full in the week of September 23, and WHO said the province was accounting for about a third of newly confirmed cases and deaths.
Speaking about the virus in that hotspot became lethal on September 27. Marie-Celestin Karondwa, acting president of the UDPS party’s federal committee in Butembo, was beaten after he went on local radio to explain prevention measures. Attackers looted his belongings and set his house on fire. He later died of his injuries. The party called him „an innocent victim for having defended the party’s position on the existence of the Ebola virus disease.“ Three days earlier, at Katula-Paida cemetery in Beni, security forces opened fire after residents demanded to see a body a burial team was preparing to inter. One person was killed and several were wounded. On Saturday, armed men attacked a hand-washing checkpoint in Beni territory and killed at least one more person.
The suspicion is older than this response. Researchers writing in BMJ Global Health found that in Ituri, mistrust arrived with the first public-health teams. Many residents accept that Ebola is real, then explain the deaths and the sudden money through an older line: Ebola is a business. Schools are both a risk and one of the few channels still open. At Bungenye Primary School in Luofu, headteacher Sister Claudine Kasoki told pupils to recognize that the disease exists and has already harmed many people.
In Bunia, after infections were confirmed in schools, mother Angèle Magani said she did not know which child came from which household, or whether anyone in that household was sick. The workforce asked to stand between those households and the virus is thinning. WHO said last week that Congo was running short of health workers. Strikes over missing pay began in July, when staff at the Rwampara center in Ituri shut the hospital and blocked the road. „We don’t know how it is possible to not have been paid for two months,“ health worker Bahati Claude said then. The same dispute has silenced checkpoints in Haut-Uélé and left engagement teams in North Kivu and Tshopo unpaid for months. Biometric checks meant to catch fictitious names on payroll lists also froze wages for people actually on the wards.
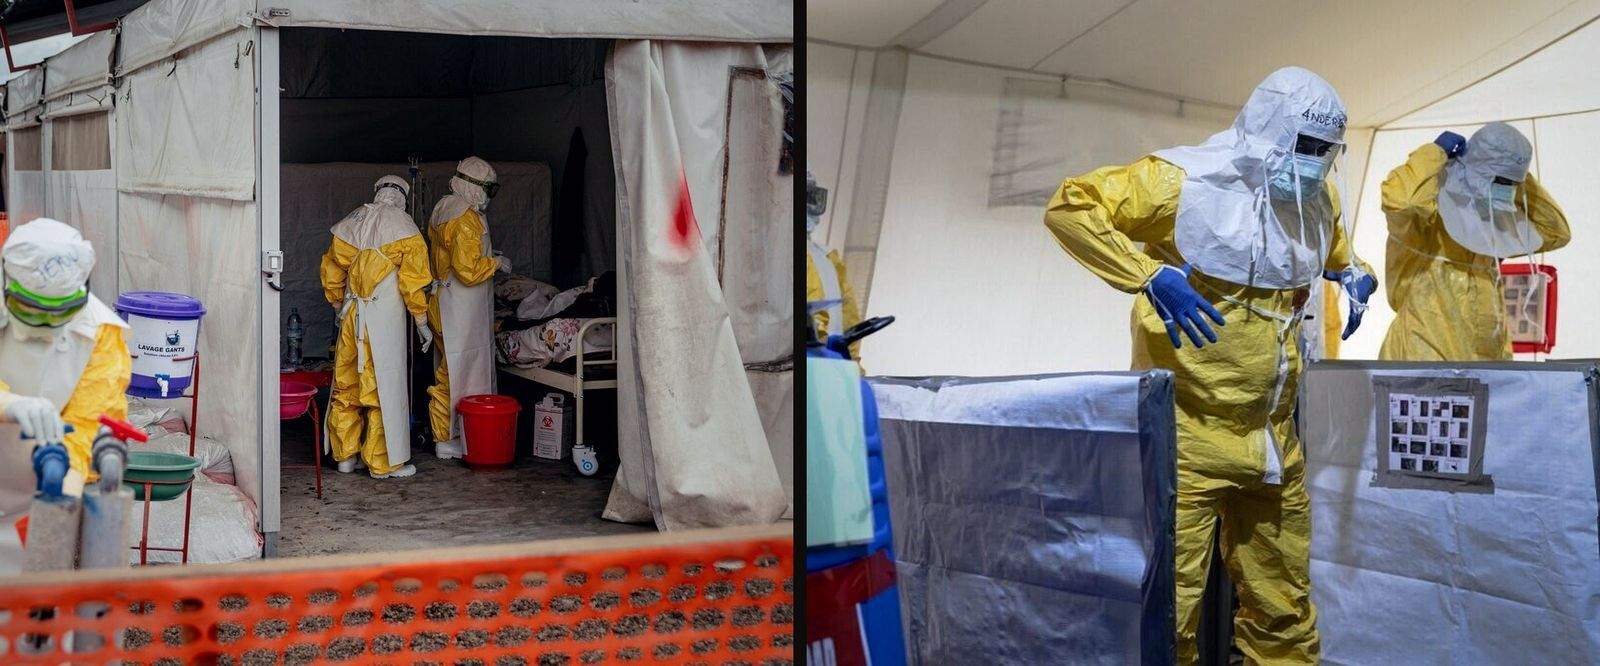
Africa CDC’s Wessam Mankoula called prompt pay a morale measure when the agency directed about $2 million toward delayed wages in July. By late September, Africa CDC’s count of health workers who had died of the virus since the outbreak was announced stood at 50. In early July the agency had already recorded 112 infected responders in Congo, 35 of them dead. After a G20-plus meeting in New York, Africa CDC said $2.9 billion had been mobilized and warned that each pledge had to be traceable to a result in an affected community. The same week, the United States was reported to be releasing a further $267 million. Both figures can be real and still leave a burial-team member in Rwampara unpaid.

Countermeasures are further behind the virus than the funding headlines imply. Ervebo, licensed against Zaire ebolavirus, is being offered to some frontline workers as a study of possible cross-protection, not as a proven Bundibugyo vaccine. By September 16, Africa CDC said 16,520 doses had reached Congo and 3,249 health and frontline workers had been vaccinated since August 27. Authorities have described a complete shortage of an experimental Bundibugyo vaccine stock in Tshopo. A trial of remdesivir and MBP134 had enrolled 479 people against a target of 1,500 to 2,500. A post-exposure study of obeldesivir had enrolled 284 of a planned 400. Candidate vaccines from Oxford, IAVI and Moderna remain early. None of that ring-fences Kisangani, a city of about 1.5 million, if the virus arrives there in force.
Speed is what separates this outbreak from the ones Congo already knows how to fight. U.S. Centers for Disease Control and Prevention researchers counted 5,458 confirmed cases and 2,606 deaths in the first 100 days after detection, May 14 through August 21. No earlier Ebola outbreak had produced more than 800 cases in its first 100 days. Africa CDC comparisons put the current epidemic far ahead of West Africa’s 2014–2016 disaster at the same point, about 7,840 cases by week 19 against 3,781 then. That earlier epidemic went on to infect more than 28,000 people and kill more than 11,000.
Outside Congo, the virus has not yet taken root. Uganda recorded about 21 confirmed and probable cases and three deaths, then completed 42 days without a new case. France confirmed one case in a physician who had worked in Ituri. Two American humanitarian workers were treated in Germany. WHO’s risk judgment remains very high inside Congo and high for neighbors. A reproduction number estimated around 1.7 needs a funeral, a mining road, or a clinic that has run out of gloves and pay.
Congo needs contact lists that contain the people who sat with the dead, wages that arrive before the next strike, and protection for anyone who says the word Ebola on a radio in Butembo. Readers who follow health reporting, Internationale Nachrichten and the wider news file at The AEGIS Alliance will recognize the pattern: a death toll becomes politically useful only after the people who could have interrupted it have already been priced out or buried themselves.